Summary
CareFlow AI is an electronic health record built around the clinician rather than the billing code. An ambient AI scribe listens to the visit, with consent, and drafts the structured SOAP note, fills the chart and queues orders while the physician talks to the patient. Clinical decision support, risk scoring, scheduling, billing and a patient portal run on the same record.
Ailoitte engineered the platform end to end: six clinical modules, the AI layer that connects them, an HL7 FHIR R4 integration layer for labs, imaging, pharmacies, payers and other EHRs, and HIPAA controls designed in from the first sprint. Practices using it report up to 70% less documentation time, 40% fewer missed alerts and a 28% better clean-claim rate.
Client-reported pilot results and industry benchmarks cited on the product page. Results vary by practice size, specialty and adoption.
About CareFlow AI
Primary care physicians spend 5.9 hours of an 11.4-hour workday inside the EHR, 1.4 of those hours before or after clinic (Arndt et al., Annals of Family Medicine, 2017). Most of the systems they use were designed in the 2000s around billing and compliance, which is why charting follows doctors home every evening.
CareFlow AI was built to reverse that: a records system where the intelligence sits in the data layer, documentation happens in the background, and the clinician’s screen shows what matters for the patient in front of them. It serves primary care, urgent care, behavioural health and telehealth practices, and can be configured per specialty.
Ailoitte built the platform as a US-market product: HIPAA-compliant, ONC-ready, with HL7 FHIR R4 interoperability as required by the 21st Century Cures Act.
EHR Systems Were Built for Billing, Not for Care
Clinicians inherit software built for a different purpose. Four problems had to be solved together, because fixing one without the others moves the burden rather than removing it.
Documentation Overload
5.9 hours a day on the EHR, manual note-taking and after-hours charting that follows physicians home.
Interoperability Gaps
Clinicians reconcile data from four to seven systems per visit: labs, imaging, pharmacy, payers and other EHRs.
Reactive, Not Predictive Care
High-risk patients deteriorate between visits because nothing watches the record when the clinician is not looking.
Compliance Complexity
HIPAA, the Cures Act, information-blocking rules and payer requirements all apply at once, and each one changes.
The Solution: A Clinical Operating System, Not Just a Records System
CareFlow AI replaces the EHR, the dictation tool, the patient portal, the billing module and the analytics dashboard with one platform. Six modules share one longitudinal patient record.
Ambient AI Documentation
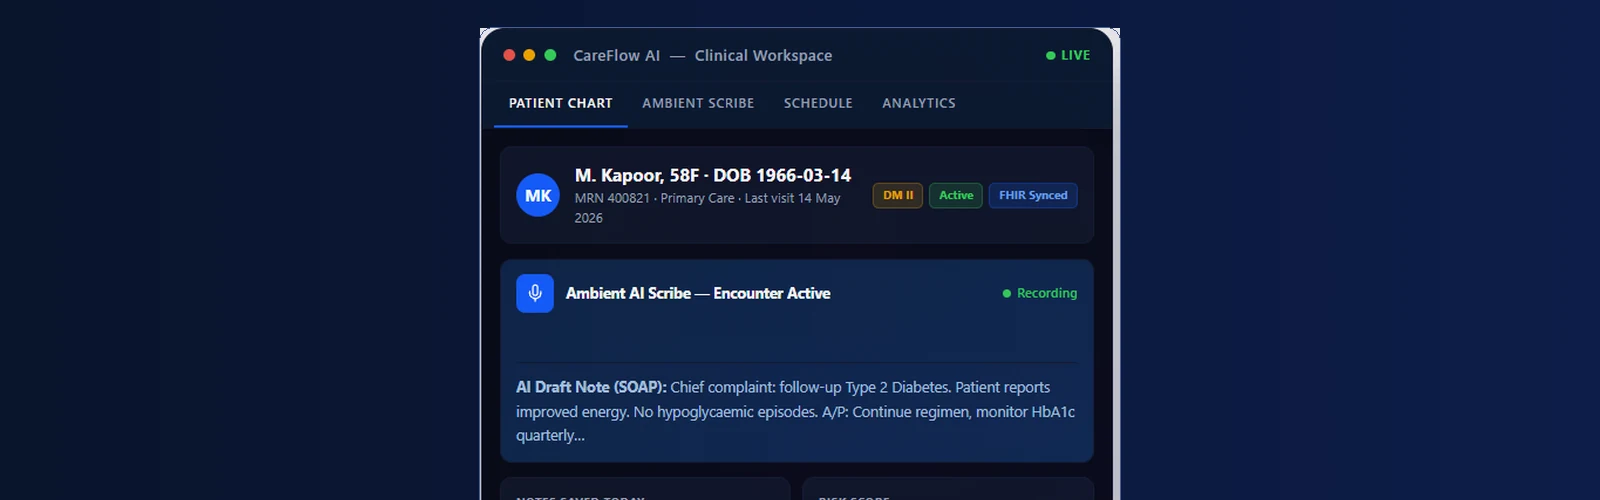
The AI scribe listens to the encounter with patient consent, drafts the SOAP note in real time, fills the EHR fields and queues orders for the physician to review and sign.
Clinical Decision Support
Real-time alerts for drug interactions, care gaps, abnormal labs and risk flags, ranked by score so that the important ones are not lost in the noise.
Patient Risk Stratification
Machine learning scores for chronic disease progression, readmission risk and preventive-care gaps, which prioritise the clinician's daily list.
Multi-Specialty Scheduling
Capacity planning, reminders, telehealth slots and no-show prediction across specialties and locations.
Revenue Cycle Management
AI-assisted ICD-10 and CPT coding, claim scrubbing before submission and denial prediction.
Patient Portal and Telehealth
Records access, booking, secure messaging and video visits on the same record the clinician uses.
CareFlow AI Core
One AI layer sits under all six modules. It brings together structured and unstructured data from across the record, and trains specialty-specific models on anonymised outcomes. Intelligence lives in the data layer rather than being bolted on to one screen.
- Python ML, large language models and a clinical knowledge graph
- Specialty-specific models trained on anonymised outcomes
- Human review before any autonomous clinical action
- Monitoring for model drift, bias and unintended consequences
Built on HL7 FHIR R4 for a Connected Care Ecosystem
Data from outside the practice is normalised, validated and routed into one encrypted longitudinal record, which every AI and clinical module reads from.
HL7 FHIR R4
A RESTful API compliant with the US Core Implementation Guide, for two-way exchange with labs, imaging, pharmacies, payers and other EHRs.
HL7 V2 and ADT Feeds
Hospital admission, discharge and transfer events, lab results and imaging orders.
SMART on FHIR and Direct Messaging
Third-party app launch with single sign-on and scoped access; encrypted referrals between providers.
Unified Longitudinal Record
PostgreSQL and a HAPI FHIR server, AES-256 encrypted, fed by Kafka event streams.
AI and Clinical Modules
Medical NLP, LLM APIs, PyTorch and Clinical BERT models behind the ambient scribe, the decision support engine, risk scoring and billing AI.
Integrations
Quest Diagnostics, Labcorp, Surescripts, DrFirst, Change Healthcare and Twilio, plus Epic, Cerner (Oracle Health), Athenahealth, eClinicalWorks, Apple Health Records and Google Health through FHIR.
Compliance Is Architecture, Not a Checklist
HIPAA, ONC and AI safety controls were designed into the platform from the first sprint and are audited quarterly.
What the Client Says
Placeholder quote: replace with the approved quote from the CareFlow AI team (40 to 80 words) and their photo before this page goes live.

Client name (to be updated), Role (to be updated), CareFlow AI
Key Outcomes
Clinical, operational and financial gains reported from pilots and the industry benchmarks the product page cites.
Less Documentation Time
Physicians reclaim 2.5 to 4 hours a day from charting.
Fewer Missed Alerts and Care Gaps
Decision support that correlates the full record and ranks alerts by score.
More Patients Seen per Physician per Day
Time freed from documentation goes back to care.
Better Clean-Claim Rate
AI coding and claim scrubbing, with denial rates falling from 15 to 20% to under 8% in pilots.
Client-reported pilot results and industry benchmarks cited on the product page (NextGen 2025, Sutter Health in JAMA Network Open, Menlo Ventures 2025). Results vary by practice size, specialty and adoption.







 India
 Job Portal